

Androgens
Testosterone
An androgen hormone with prescription uses and important differences between replacement therapy and nonmedical use.
Established medical uses
Also known as: test · TRT
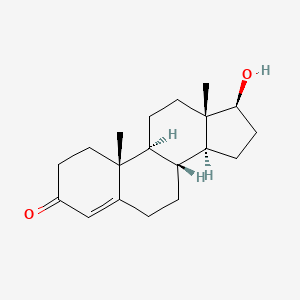
Practical use
Applying the explained evidence
- Where it fits
- An androgen hormone with prescription uses and important differences between replacement therapy and nonmedical use.
- Put the information into practice
- Discuss fertility goals, blood pressure, other medicines and relevant medical history before treatment decisions. Monitoring can identify some problems; normal results cannot rule out every risk.
- Formulation and purpose
- Write down the exact compound and formulation behind a claim. Compare the studied population and purpose with the situation being discussed; evidence for medical replacement does not automatically answer a physique-enhancement question.
- Keep this limit in view
- A supervised group mean is a research result. It does not determine an individual outcome, the amount of actual muscle, or how much would be retained.
Overview
Testosterone is an androgen involved in sexual development and other body functions. Prescription testosterone can replace deficient hormone production in appropriately diagnosed patients. A medical replacement indication does not establish that a bodybuilding cycle is safe.
Risks and limitations
Potential concerns include increased blood pressure, reduced sperm production and changes in mood. Higher-than-prescribed use carries additional serious risks. The formulation and medical history matter; an oral product guide cannot describe every injectable or topical preparation.
How to read this
Discuss fertility goals, blood pressure, other medicines and relevant medical history before treatment decisions. Monitoring can identify some problems; normal results cannot rule out every risk.
Research explained
Muscle size and strength: the 1996 controlled experiment
Who was studied
43 healthy men in four randomized groups, separating testosterone/placebo from resistance training/no training; 10 weeks.
- Fat-free mass change
- 6.1 kg
- Bench-press change
- 22 kg
- Squat-capacity change
- 38 kg
What was found
With testosterone plus training, fat-free mass increased by 6.1 kg on average; bench-press strength increased 22 kg and squat capacity 38 kg. Muscle cross-sectional area also increased. These are changes within that study group, not placebo-adjusted promises.
What it cannot establish
The trial was small and short. Fat-free mass includes more than muscle tissue. A group mean does not tell us the range of individual outcomes or what remains after treatment ends. It was not designed to quantify uncommon cardiovascular events or long-term fertility outcomes.
Read the original studyTRAVERSE: cardiovascular events during medical replacement
Who was studied
5,246 men aged 45–80 with symptoms, two low fasting testosterone results, and existing or elevated cardiovascular risk. Testosterone gel was compared with placebo; average follow-up was 33 months.
- Testosterone: primary events
- 7 %
- Placebo: primary events
- 7.3 %
What was found
The primary cardiovascular composite occurred in 7.0% versus 7.3%; hazard ratio 0.96, 95% confidence interval 0.78–1.17. The prespecified noninferiority criterion was met. Atrial fibrillation, acute kidney injury and pulmonary embolism occurred more often in the testosterone group.
What it cannot establish
This tested supervised replacement, not bodybuilding exposure, other formulations, or combinations. Noninferiority for the primary composite is not evidence that every adverse outcome is unchanged. The confidence interval includes both lower and higher relative hazards.
Read the original studyMedical replacement and enhancement are different evidence questions
Testosterone is a hormone with prescription replacement indications in people with deficient production associated with a medical condition. It is also used nonmedically at exposures that medical replacement trials did not evaluate. The name on the bottle does not make those two settings equivalent.
FDA lists multiple delivery forms, including injections, topical preparations and oral products. A clinical result belongs to the studied formulation, population and purpose. It should not automatically be transferred to another form or to a different goal.
Supporting sourceHow to interpret the cardiovascular labeling change
In February 2025, FDA directed removal of the boxed-warning language about increased cardiovascular outcomes after its review of TRAVERSE. At the same time, ambulatory blood-pressure studies led to class-wide blood-pressure warning changes.
Those two decisions address different evidence. A reassuring result for a trial’s composite endpoint does not make a rise in blood pressure irrelevant, and neither decision establishes the safety of high-dose nonmedical use. The age-related limitation-of-use language was retained.
Supporting sourcePharmacokinetics: there is no single testosterone half-life
The cited intramuscular cypionate label gives an approximate half-life of eight days. This reflects that ester and depot preparation, not every testosterone product. A half-life is a pharmacokinetic measurement; it is not a schedule for self-treatment or a timer for recovery of natural hormone production.
When comparing numbers, check the ester, delivery route and whether the reported quantity describes absorption from a depot or elimination from circulation. Those distinctions matter more than a single number copied into a comparison chart.
Supporting sourceClaims versus findings
Not established
The muscle-study average predicts my own gains.
A supervised group mean is a research result. It does not determine an individual outcome, the amount of actual muscle, or how much would be retained.
Check the evidenceIncorrect interpretation
The updated FDA warning means all testosterone use is heart-safe.
The update concerns medical products and evidence from replacement treatment. FDA simultaneously required stronger blood-pressure information.
Check the evidenceLearn with Avery
The Truth About Your First Test Cycle — Complete Protocol, PCT, and What to Actually Expect
Total testosterone and how you feel
Why testosterone results are not automatic
A high total testosterone result with persistent symptoms
Reading testosterone alongside other blood markers
Testosterone, red blood cells and iron stores
Same testosterone number, different context
What a training clip cannot tell you about testosterone
Why a testosterone screenshot is not a treatment target
HGH and testosterone: expectations
First Testosterone Cycle: What to Understand First · Member Classroom lesson
Testosterone, Estrogen & Hormone Feedback · Member Classroom lesson
Sources
MedlinePlus: testosterone (oral formulation)
Muscle size and strength: the 1996 controlled experiment
FDA: 2025 testosterone labeling changes
TRAVERSE: cardiovascular events during medical replacement
Testosterone cypionate product label
Sources checked 2026-09-28.
General education; not a personal treatment plan.